Your shopping cart is empty!

How much inositol is in a daily serving and why are doses higher in studies?
Published: 15/10/2026
Times Read: 73
Comments : 0
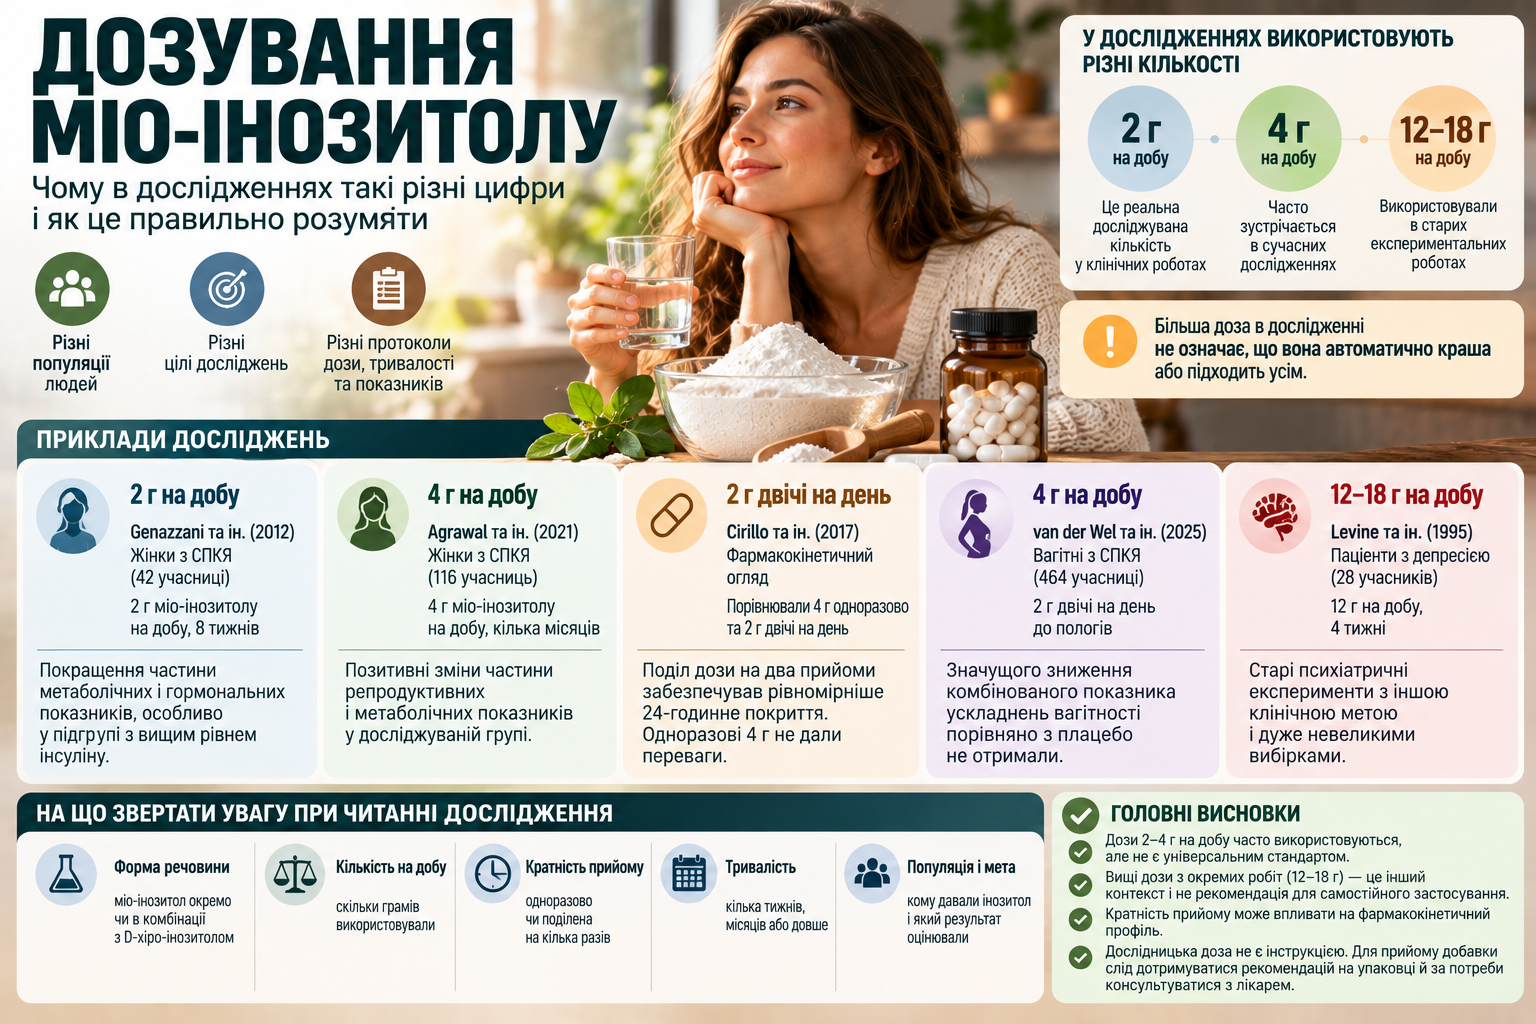
Myo-inositol studies have come up with very different numbers: 2g/day, 4g/day, and even 12-18g/day in older studies. This does not mean that there is a simple “more = better” scale or that the highest amount studied is automatically the right amount for everyday use.
The dose in scientific work is part of a specific protocol: it is chosen for a specific population, purpose, duration, and endpoint. Therefore, a number from one study cannot be taken out of context and turned into a universal dosing regimen.
Why there is no single “scientific dose” for myo-inositol
Myo-inositol studies have been conducted in different groups of people and with very different goals. Some studies have looked at metabolic and reproductive parameters, others at pharmacokinetics, and older psychiatric experiments have used very different amounts.
Therefore, the statement “the studies used 4 g” is incomplete. At least five things need to be clarified: what form of inositol was used, how much per day, how this amount was divided throughout the day, how long the protocol lasted, and what exactly was measured.
What studies show with 2g per day
In a study by Genazzani et al., 42 women with polycystic ovary syndrome received myo-inositol 2 g/day for 8 weeks. The authors assessed metabolic and hormonal parameters and reported changes in some of them, especially in the subgroup with higher baseline insulin levels.
For the topic of dosage, the important fact here is that 2g per day is a real amount that has been used in human research. However, one study in a specific population does not establish a universal dose for all purposes.
Why is 4g per day often found in the literature?
Many modern studies have used a total daily dose of 4 g of myo-inositol. For example, in a randomized trial of 116 women with polycystic ovary syndrome, one group received 4 g of myo-inositol per day for several months.
But the prevalence of a particular number in the literature does not automatically make it optimal. Often, researchers use a scheme that has already been seen in previous works so that the results can be compared.
2g twice a day and 4g once are not exactly the same
A pharmacokinetic review by Cirillo et al. highlighted that for myo-inositol, it is not only the total daily dose that is important, but also the way it is distributed. Based on available pharmacokinetic data, a single 4 g dose did not provide any advantage over a 2 g twice-daily regimen, while a split dose provided more uniform 24-hour coverage.
This is not a recommendation to take myo-inositol in a specific way. It is an example of why the same total amount can have a different pharmacokinetic profile depending on the frequency of administration.
Why 4g cannot be called a universally optimal dose
A true dose-response conclusion requires studies where multiple doses are systematically compared in the same population, over the same time period, and on the same endpoints. There is no such comprehensive basis for myo-inositol.
A 2024 systematic review prepared for international guidelines on polycystic ovary syndrome included 30 trials with 2230 participants. The authors found some positive signals, but overall assessed the evidence base as limited and heterogeneous.
The 2023 international guidelines do not establish a specific type, dose, or combination of inositol as a universal standard because of this uncertainty.
A large 2025 study shows why a higher dose does not guarantee an effect
A large double-blind study in 2025 involved 464 pregnant women with polycystic ovary syndrome. The active group received 2 g of myo-inositol twice daily along with folic acid from early pregnancy until delivery.
The primary outcome was a composite of three pregnancy complications. There was no significant reduction in this composite compared with placebo.
For an article on dosage, this is an important example: even the well-known regimen of 4 g per day in a large modern study did not guarantee a positive result for a specifically chosen clinical goal.
Where did the 12–18 g per day figure come from in the literature?
Inositol was studied in small psychiatric experiments in the 1990s and early 2000s. In a 1995 double-blind study, 28 depressed patients were given 12 grams of inositol per day or a placebo for four weeks.
Another small crossover study used up to 18 g/day in panic disorder. Such numbers often seem impressive when seen without context.
But these are old experimental protocols, a different clinical goal, and very small sample sizes. They do not establish a universal daily amount of myo-inositol and are not a guideline for self-administration.

Why the research dose is not a guideline
Therefore, the phrase "the study used 4 g" only means that this is the amount that was part of the particular experiment. It does not mean "everyone needs 4 g."
Similarly, very high doses from older studies do not become more acceptable just because they are published in a scientific journal. The context of the study is always more important than the individual number.
Myo-inositol and D-chiro-inositol cannot be considered as the same scheme
In modern works, one can find both myo-inositol alone and in combinations with D-chiro-inositol. The total mass of such a mixture by itself does not describe the ratio of the two isomers and does not allow one protocol to be equated with another.
Therefore, when reading a study, you need to look not only at the number in grams, but also at what form of inositol was used.
What quantities were actually used in the studies?
| Context | Number in the study | Scheme in operation | What does this show? |
|---|---|---|---|
| PCOS, 8 weeks | 2 g/day | Myo-inositol for 8 weeks | 2 g is the actual amount studied |
| PCOS, several months | 4 g/day | Myo-inositol as one of the regimens being studied | 4g is often used in modern works |
| Pharmacokinetics | 4 g/day | 4 g once compared to 2 g twice | Multiplicity can change the concentration profile |
| Pregnancy + PCOS, 2025 | 4 g/day | 2 g twice daily until delivery | A higher test quantity does not guarantee a positive result. |
| Old psychiatric works | 12–18 g/day | Brief experimental protocols | Historical fact, not a modern admission scheme |
How to read a dose correctly in a scientific article
- Form of substance: myo-inositol alone or in combination with other isomers.
- Total amount: how many grams or milligrams were received per day.
- Multiplicity: the entire amount at once or divided into several doses.
- Duration: several weeks, months or longer.
- Population and endpoint: who was given inositol and what outcome were they trying to test.
Frequently asked questions
What dose of myo-inositol is most often used in studies?
2–4 g/day is often found in current literature, but the specific amount depends on the population, purpose, and study design. This does not establish a one-size-fits-all regimen.
Is 4g of myo-inositol better than 2g?
There is no such universal conclusion. For a reliable comparison, a full dose-dependent database under the same conditions is needed, and it is limited.
Why did some studies use 2 g twice daily?
This distribution has been studied, in particular, through the pharmacokinetic profile. A review of the available data did not show an advantage of a single 4 g dose over 2 g twice daily in terms of duration of coverage.
Can we focus on the maximum dose that was once studied?
No. The maximum experimental number is not a recommended number. It is specific to the protocol, population, and clinical question.
Why did the old studies give 12–18 g of inositol?
These high amounts have been used in small psychiatric experiments. They belong to a different research context and do not define the usual use of myo-inositol.
Is the total dose of myo-inositol and a mixture of myo- and D-chiro-inositol the same?
No. In a combination, it is not only the total grams that are important, but also the amount of each isomer and their ratio.
How do I know if the dose from the study is suitable for regular use?
You should not undergo the research protocol on your own. For supplements, you should follow the instructions on the packaging, and if you have medical conditions, discuss use with your doctor.
Sources
- Genazzani AD and others. (2012). Differential insulin response to myo-inositol administration in obese polycystic ovary syndrome patients. Gynecological Endocrinology. PubMed
- Cirillo F. and others. (2017). Finding the best therapeutic approach for PCOS: the importance of inositol(s) bioavailability. European Review for Medical and Pharmacological Sciences. PubMed
- Agrawal A. and others. (2021). Impact of myoinositol with metformin and myoinositol alone in infertile PCOS women undergoing ovulation induction cycles — randomized controlled trial. Gynecological Endocrinology. PubMed
- van der Wel AWT and others. (2025). Myo-inositol Supplementation to Prevent Pregnancy Complications in Polycystic Ovary Syndrome: A Randomized Clinical Trial. JAMA. PubMed
- Fitz V. and others. (2024). Inositol for Polycystic Ovary Syndrome: A Systematic Review and Meta-analysis to Inform the 2023 Update of the International Evidence-based PCOS Guidelines. Journal of Clinical Endocrinology & Metabolism. PubMed
- Teede HJ and others. (2023). Recommendations from the 2023 International Evidence-based Guideline for the Assessment and Management of Polycystic Ovary Syndrome. Human Reproduction. PubMed
- Levine J. and others. (1995). Double-blind, controlled trial of inositol treatment of depression. American Journal of Psychiatry. PubMed
- Palatnik A. and others. (2001). Double-blind, controlled, crossover trial of inositol versus fluvoxamine for panic disorder. Journal of Clinical Psychopharmacology. PubMed
Dietary supplement. Not a medicine. Consult a doctor before use.
Products related to this post


Related Posts
Comments
Information
Customer Service
Extras
My Account


Sports nutrition manufacturer in Ukraine StarkPharm © 2026


