Your shopping cart is empty!

Chondroitin: Why Studies Give Conflicting Results
Published: 07/11/2026
Times Read: 71
Comments : 0
Chondroitin sulfate is a connective tissue compound that is often found in joint supplements. But the scientific literature is mixed on it, with some clinical trials finding no difference from placebo, others finding no convincing effect, and professional associations’ recommendations diverging. This is not a random controversy surrounding a single experiment: the outcome is influenced by the form of the substance, the quality of the sample, the characteristics of the participants, and the way changes are measured.
The main question is not whether chondroitin is present in cartilage, it is a biochemical fact. What is important is whether the specific form studied gives a noticeable result to a person after taking it. And why a positive conclusion for one standardized preparation cannot be automatically transferred to any supplement with the same name.

Why the findings on chondroitin are so different: a brief comparison
| Factor | What may vary between studies | How does this affect the conclusion? |
|---|---|---|
| Sample composition | Purity, actual content, molecular weight and origin of chondroitin | The same name does not mean chemically identical material |
| Design | Randomization, blinding, placebo control, and risk of bias | A less robust design may overestimate the effect |
| Participants | Joint, initial symptoms, age and severity of changes | The result for the knee does not necessarily transfer to the hand or hip |
| Indicator | Pain, daily function, X-ray slit lamp or MRI | A statistical change in one parameter does not equal a significant improvement in all |
| Duration | A few weeks versus months of observation | Research can answer various time questions |
| Data analysis | Selection of works, assessment of their quality and method of unification | Reviews sometimes come to disparate average ratings |
In scientific analysis, each of these factors is important. When two studies have different results, it is worth finding out whether they tested the same material, in similar people, using the same criteria , rather than immediately declaring one of the works to be erroneous.
What does the name "chondroitin sulfate" really mean?
Chondroitin sulfate belongs to glycosaminoglycans - long chains of repeating sugar units with sulfate groups. In the cartilage matrix, these structures are associated with proteoglycans: they help the tissue retain water and withstand loads. Hence the interest in chondroitin as an ingredient for joints.
However, chondroitin from different sources is not necessarily the same. The average chain length, the position of the sulfate groups, the composition of the accompanying substances and the degree of purification differ. Such details are not visible just from the inscription "chondroitin sulfate" on the label. This is important for laboratory comparison of compositions, but the analysis of purity alone does not yet prove the benefit to humans.
Martel-Pelletier et al. (2015) described the varying properties of chondroitin preparations and drew attention to origin and purification. A critical review by Brito et al. (2023) also highlights that not all commercial chondroitin samples can be considered interchangeable and the strength of the clinical evidence is still limited.
Why supplement research can't be equated with a clinical trial
In the paper Comparative Analyses of Pharmaceuticals or Food Supplements Containing Chondroitin Sulfate by Stellavato et al. (2019), the authors compared ten European food supplements and two pharmaceuticals. According to laboratory analysis, the chondroitin content in nine out of ten supplements was lower than claimed. The researchers also compared the responses of cells in the laboratory.
This is important evidence of the variability of the specific samples selected. But it does not follow that all supplements contain less of the substance than is stated, or that the laboratory reaction of the cells automatically predicts the result for a human knee or hand. The conclusion is much narrower: confirmation of composition and standardization are necessary for fair comparison of studies.
In another analysis of products for the US market by Stellavato et al. (2021), researchers reported discrepancies between declared and measured content in a small sample. Such studies explain a potential reason for non-reproducibility of results, but are not a substitute for randomized trials in humans.
What the CONCEPT trial showed: a positive result with an important condition
In a study by Reginster et al. (2017), known as CONCEPT, standardized pharmaceutical-grade chondroitin sulfate, celecoxib, and placebo were compared in adults with symptomatic knee osteoarthritis. The trial lasted six months; the chondroitin group used 800 mg/day. These data are presented as parameters of the study protocol and not as advice for self-administration.
However, even a good, positive test doesn’t answer all the questions. It doesn’t test dozens of other formulations, doesn’t determine the benefits for each consumer, and doesn’t make all combinations of chondroitin equivalent to the tested form. That’s why the ingredient name can’t be taken as proof that different products will perform the same way.
Why large reviews evaluate the result more conservatively
A Cochrane systematic review by Singh et al (2015) pooled the studies of chondroitin in osteoarthritis. In some short-term comparisons, the authors found small mean differences in pain. However, the quality of the evidence was mixed, and the conclusions became more cautious when focusing on studies with more robust designs.
A network meta-analysis by Wandel et al. (2010), published in the BMJ, reviewed large trials of glucosamine, chondroitin, and their combination. The researchers concluded that the mean differences from placebo for pain did not reach the pre-specified threshold for a clinically important difference. The analysis included a variety of research designs, and the assessment of funding indicated smaller effects in independent studies.
This is not a direct refutation of CONCEPT: a single test of a specific form and a meta-analysis of a heterogeneous set of studies answer somewhat different questions. But the reverse conclusion would also be false: a positive result of one formula does not dispel doubts about the average effect in a broader data set.
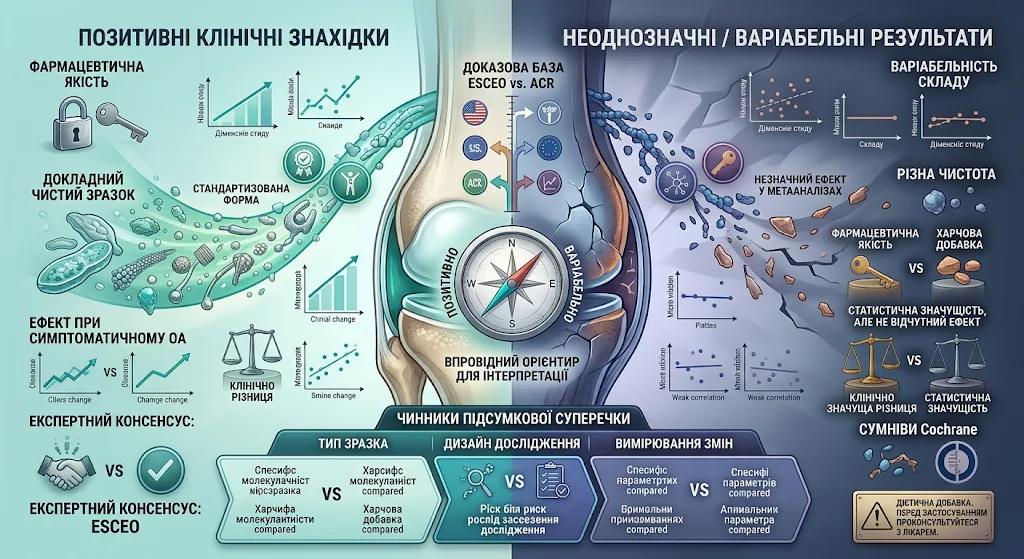
Pain, mobility and cartilage structure - different results
Pain is assessed primarily by participant responses to scales, function by ability to perform daily activities, and structural changes by imaging. These measurements are not interchangeable. A participant may experience improvement but have no measurable structural change; the opposite is also possible, where a small difference in imaging is not accompanied by a significant improvement in well-being.
A pilot study by Wildi et al. (2011) used MRI to assess cartilage and bone marrow in the knee joint; the chondroitin group received 800 mg/day for six months with follow-up. The authors found differences in individual structural parameters, but symptoms were similar between groups. The small sample size and specific assessment methodology do not allow us to translate this result into a general promise of cartilage repair.
In a practical reading of a study, it is important to ask three questions: what exactly was measured, how big the change was, and can a person feel it. The mere fact of statistical significance does not answer all three.
Why the recommendations of professional societies do not coincide
Different expert groups may review partially identical papers and reach different conclusions due to different criteria: which studies to include, how much weight to give to risk of bias, whether to consider only standardized pharmaceutical forms, and what level of evidence to consider sufficient.
Thus, the American College of Rheumatology/Arthritis Foundation guidelines (Kolasinski et al., 2020) advise against the use of chondroitin sulfate in knee and hip joint changes, but allow its conditional use in hand joints. In contrast, the ESCEO expert algorithm (Bruyère et al., 2019) gives a more positive assessment to pharmaceutical chondroitin sulfate for the knee and separates it from products with less controlled composition.
This does not mean that scientists disagree on the basic facts. They differ in their assessment of how convincingly the available results support clinically meaningful benefits and whether they can be transferred to a wide range of agents.
How to read chondroitin research without drawing false conclusions
Start with the exact form: is the source, standardization, and characteristics of the substance stated? Next, look for the placebo control, method of randomization, and duration of follow-up. Pay particular attention to how the authors defined success—by subjective pain, function, or structural measures.
Equally important are the size of the groups, the proportion of participants who completed the study, and potential conflicts of interest. Industry funding does not automatically make the work unreliable, but it does require a closer examination of independent confirmation of the results. Findings that are replicated in several high-quality trials should be preferred over a flashy quote from a single study.
If the label lists a complex with glucosamine, MSM, collagen, or other components, it is more difficult to determine the contribution of chondroitin itself. Data on a single substance cannot be automatically attributed to a mixture, and vice versa. The issue of combinations has a separate evidentiary logic; it is not identical to the issue of the quality and inconsistency of studies on a single ingredient.
Caution: Who should discuss chondroitin with their doctor?
Chondroitin should not be used by children and adolescents, pregnant or breastfeeding women. People with diabetes, prediabetes, asthma, and those who need to monitor their sodium, potassium, or calcium intake should also consult a healthcare professional before taking a supplement. If joint pain worsens, swelling, redness, limited movement, or an injury occurs, it is important to determine the cause of the symptoms rather than relying on the supplement's advertising.

Conclusion: Inconsistency does not mean that all research is the same
Chondroitin has a real biological role in connective tissue, but the clinical benefit of supplementing with it remains a matter of debate. The best explanation for the discrepancies is a combination of varying sample quality, design, and different metrics and methods of generalization. Some trials of specific standardized forms have been positive, but large independent analyses and professional recommendations do not support the unequivocal promises of all products.
It is more useful for the reader to look not for a yes or no answer without details, but for the connection between a specific compound, a study, and a measured outcome. This is how scientific data can be interpreted without being overly optimistic and without unfairly denying individual observations.
Frequently asked questions
Why are some chondroitin studies positive and others not?
They may differ in the composition of the material, the quality of the methodology, the participants, and the outcome they assessed. Therefore, different conclusions do not necessarily indicate a flaw in one of the studies.
Is chondroitin the same in all supplements?
No. Origin, purification, molecular characteristics, and actual content may vary. These differences cannot be determined by the ingredient name.
Is chondroitin proven to restore cartilage?
Some small trials have shown differences in imaging findings, but they do not prove cartilage repair in any individual after taking any supplement.
What is a clinically significant difference?
This is the amount of change that is considered significant enough for a person, rather than simply being statistically different from zero. This is why a significant result in an analysis does not always mean a tangible benefit.
Why are the US and European recommendations different?
Expert groups apply different criteria for selecting and weighing evidence, and also evaluate specific standardized forms of chondroitin differently.
Does a positive CONCEPT result mean that any chondroitin is effective?
No. This trial evaluated a specific form and a specific group of participants. It is incorrect to generalize the results to all commercial products.
Can chondroitin replace counseling for joint pain?
No. The causes of pain vary, and the results of ingredient studies do not replace a medical examination and individual recommendations.
What should you look for first in a scientific article about chondroitin?
On the type of drug, control group, number of participants, duration, main effect indicator and possible conflicts of interest.
Sources
- Singh JA et al. (2015). Chondroitin for osteoarthritis. Cochrane Database of Systematic Reviews, CD005614. PubMed.
- Wandel S. et al. (2010). Effects of glucosamine, chondroitin, or placebo in patients with osteoarthritis of the hip or knee: network meta-analysis. BMJ, 341, c4675. PubMed.
- Reginster J.-Y. et al. (2017). Pharmaceutical-grade Chondroitin sulfate is as effective as celecoxib and superior to placebo in symptomatic knee osteoarthritis: the CHONdroitin versus CElecoxib versus Placebo Trial (CONCEPT). Annals of the Rheumatic Diseases, 76(9), 1537–1543. PubMed.
- Kolasinski SL et al. (2020). 2019 American College of Rheumatology/Arthritis Foundation Guideline for the Management of Osteoarthritis of the Hand, Hip, and Knee. Arthritis Care & Research, 72(2), 149–162. PubMed.
- Brito et al. (2023). Chondroitin Sulfate Supplements for Osteoarthritis: A Critical Review. Nutrients. PubMed.
- Martel-Pelletier J. et al. (2015). Discrepancies in composition and biological effects of different formulations of chondroitin sulfate. Molecules. PubMed.
- Wildi LM et al. (2011). Chondroitin sulphate reduces both cartilage volume loss and bone marrow lesions in knee osteoarthritis patients starting as early as 6 months after initiation of therapy: a randomized, double-blind, placebo-controlled pilot study using MRI. Annals of the Rheumatic Diseases, 70(6), 982–989. PubMed.
- Bruyer O. et al. (2019). An updated algorithm recommendation for the management of knee osteoarthritis from the European Society for Clinical and Economic Aspects of Osteoporosis, Osteoarthritis and Musculoskeletal Diseases (ESCEO). Seminars in Arthritis and Rheumatism, 49(3), 337–350. PubMed.
- Stellavato A. et al. (2019). Comparative Analyzes of Pharmaceuticals or Food Supplements Containing Chondroitin Sulfate: Are Their Bioactivities Equivalent? Advances in Therapy, 36, 3221–3237. PubMed.
- Stellavato A. et al. (2021). Chondroitin Sulfate in USA Dietary Supplements in Comparison to Pharma Grade Products: Analytical Fingerprint and Potential Anti-Inflammatory Effect on Human Osteoarthritic Chondrocytes and Synoviocytes. Pharmaceutics, 13(5), 737. PubMed.
Dietary supplement. Not a medicine. Consult a doctor before use.
Products related to this post



Related Posts
Comments
Information
Customer Service
Extras
My Account


Sports nutrition manufacturer in Ukraine StarkPharm © 2026


